
ANCA Associated Vasculitis
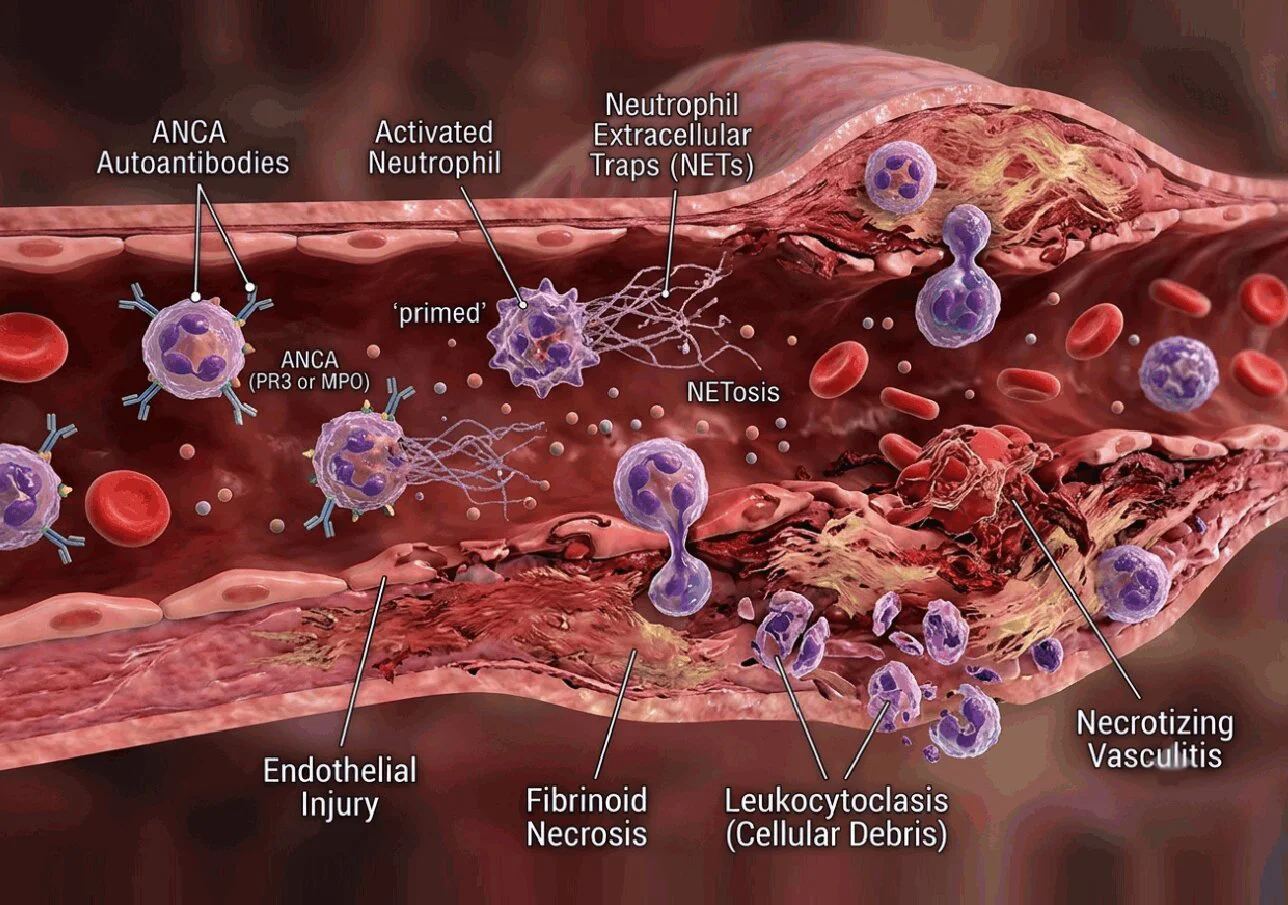
ANCA Associated Vasculitis
ANCA-Associated Vasculitis: Symptoms, Diagnosis and Treatment
ANCA-associated vasculitis (AAV) is a group of autoimmune diseases in which inflammation affects small blood vessels. The group includes granulomatosis with polyangiitis, microscopic polyangiitis and eosinophilic granulomatosis with polyangiitis. The kidneys, lungs, upper airways, skin, nerves and other organs may be affected. Disease severity ranges from limited to organ-threatening. If you are researching anca associated vasculitis treatment in dwarka, it is useful to understand how the condition is assessed, which treatment approaches may be considered and why follow-up is important. Medical care should be based on an individual's symptoms, examination findings, test results, other health conditions and preferences. Information on this page is educational and cannot replace an in-person assessment or an individual treatment plan.
What Is ANCA-Associated Vasculitis?
ANCA-associated vasculitis (AAV) is a group of autoimmune diseases in which inflammation affects small blood vessels. The group includes granulomatosis with polyangiitis, microscopic polyangiitis and eosinophilic granulomatosis with polyangiitis. The kidneys, lungs, upper airways, skin, nerves and other organs may be affected. Disease severity ranges from limited to organ-threatening. The name describes a specific disease pattern, but the way it affects each person can be different. Some people have symptoms limited mainly to one organ system, while others develop features involving several parts of the body. Disease activity may change over time. A clinician considers the pattern, duration and severity of symptoms rather than making a decision from one symptom or laboratory result.
Common Symptoms and Warning Signs
Symptoms associated with anca-associated vasculitis may include persistent sinus or ear symptoms, nosebleeds, cough, breathlessness, coughing blood, fatigue, fever, weight loss, skin purpura, numbness or weakness, blood in urine and swelling. Kidney inflammation may be present without obvious symptoms, so urine and kidney function testing are important.. The presence of one or more of these features does not automatically confirm the condition. Similar symptoms can occur in other illnesses, and the pattern over time is often important.
Possible Causes and Risk Factors
The causes of anca-associated vasculitis are not always fully understood. Current medical knowledge points to the precise cause is not fully understood. Immune dysregulation and antibodies directed against neutrophil components are involved in many cases. PR3-ANCA and MPO-ANCA are the main antibody patterns, but some patients are ANCA-negative. A positive ANCA test alone does not prove active vasculitis. Risk factors are not the same as a definite cause: many people with a recognised risk factor never develop the disease, and some people develop it without an obvious risk factor. A clinician may ask about family history, medicines, previous illnesses, environmental exposures and other autoimmune symptoms to understand the broader context.
How Is the Condition Diagnosed?
Assessment for anca-associated vasculitis may include clinical assessment, ANCA testing, blood counts, inflammatory markers, kidney function, urine microscopy, chest imaging and other organ-specific investigations. Biopsy of an affected tissue, such as kidney, skin or lung when appropriate, can help confirm the diagnosis and distinguish other causes. The exact investigations depend on the symptoms and organs that may be involved. Not every person needs every test. Results must be interpreted alongside the clinical examination, because isolated abnormalities can occur for reasons unrelated to the suspected disease.
Treatment Options for ANCA-Associated Vasculitis
Treatment for anca-associated vasculitis is individualised. Depending on the diagnosis and severity, approaches may include management depends on the specific diagnosis and whether organs are threatened. Induction therapy may include glucocorticoids with rituximab or cyclophosphamide in severe disease; selected less severe cases may use other regimens. Maintenance treatment may include rituximab, azathioprine or other medicines. Infection prevention and monitoring are integral parts of care. The goal may be to reduce inflammation, control symptoms, prevent organ damage, preserve function or manage complications. Not every treatment is suitable for every patient, and some medicines require blood tests, infection screening or other safety checks before and during use.
Lifestyle and Long-Term Management
Supportive measures for people living with anca-associated vasculitis may include adhering to monitoring, reporting infection symptoms, avoiding smoking, maintaining suitable activity and discussing vaccination before or during immunosuppression. Blood pressure, kidney function, bone health and cardiovascular risk should be reviewed. Medicines should not be stopped or changed without the treating team. These measures complement, rather than replace, medical treatment when treatment is indicated. The right level of activity, dietary changes and monitoring will depend on the person's health and the organs involved.
Possible Complications
Potential complications of anca-associated vasculitis include kidney failure, lung haemorrhage, peripheral nerve injury, skin damage and other organ complications. Relapses can occur, so follow-up may continue even after symptoms improve. Treatment itself can also increase infection and other medicine-related risks. Complications are not inevitable, and their likelihood depends on the disease subtype, duration, activity, co-existing conditions and response to treatment. Monitoring is intended to identify changes early and to balance disease control against possible medicine-related effects.
When Should You Seek Medical Advice?
Medical evaluation is appropriate for coughing blood, sudden breathlessness, reduced urine output, blood in urine, new weakness or numbness, severe abdominal pain or visual symptoms. These may require urgent assessment, particularly in someone with known or suspected AAV. Anyone with a known diagnosis should follow the monitoring schedule advised by their clinician, even when symptoms are stable. New symptoms should be discussed rather than assumed to be part of the existing condition. Severe or rapidly worsening symptoms may require urgent or emergency assessment.
Conclusion
ANCA-Associated Vasculitis can affect people in different ways, so assessment and management need to be tailored to the individual. Understanding the symptoms, diagnostic process, treatment choices and possible complications can help patients take part in informed discussions about their care. Regular follow-up, appropriate investigations and a plan that reflects disease activity are important parts of long-term management. The information in this article is general and should be discussed with a qualified healthcare professional in the context of an individual's circumstances.
Frequently Asked Questions (FAQs)
What is anca-associated vasculitis?
ANCA-associated vasculitis (AAV) is a group of autoimmune diseases in which inflammation affects small blood vessels. The group includes granulomatosis with polyangiitis, microscopic polyangiitis and eosinophilic granulomatosis with polyangiitis. The kidneys, lungs, upper airways, skin, nerves and other organs may be affected. Disease severity ranges from limited to organ-threatening. The exact features and severity vary, so assessment is based on the individual's clinical history, examination and relevant investigations.
What are common symptoms?
Symptoms may include persistent sinus or ear symptoms, nosebleeds, cough, breathlessness, coughing blood, fatigue, fever, weight loss, skin purpura, numbness or weakness, blood in urine and swelling. Kidney inflammation may be present without obvious symptoms, so urine and kidney function testing are important. Similar features can occur in other conditions, so persistent or unexplained symptoms should be medically assessed.
How is the condition diagnosed?
Assessment may include clinical assessment, ANCA testing, blood counts, inflammatory markers, kidney function, urine microscopy, chest imaging and other organ-specific investigations. Biopsy of an affected tissue, such as kidney, skin or lung when appropriate, can help confirm the diagnosis and distinguish other causes. No single result should generally be interpreted in isolation; the findings are considered alongside symptoms and examination.
What treatments may be used?
Depending on severity and the organs involved, treatment may include management depends on the specific diagnosis and whether organs are threatened. Induction therapy may include glucocorticoids with rituximab or cyclophosphamide in severe disease; selected less severe cases may use other regimens. Maintenance treatment may include rituximab, azathioprine or other medicines. Infection prevention and monitoring are integral parts of care. The appropriate plan is individualised and requires medical supervision.
Can lifestyle changes replace medical treatment?
Lifestyle measures may support general health and symptom management, but they do not replace prescribed treatment when a clinician considers disease-modifying or organ-protective therapy necessary.
When should someone seek urgent medical care?
Seek prompt assessment for coughing blood, sudden breathlessness, reduced urine output, blood in urine, new weakness or numbness, severe abdominal pain or visual symptoms. These may require urgent assessment, particularly in someone with known or suspected AAV. If symptoms are severe, sudden or rapidly worsening, use local emergency services.


